Bicornuate Uterus: What It Means for Pregnancy, Fertility and Delivery
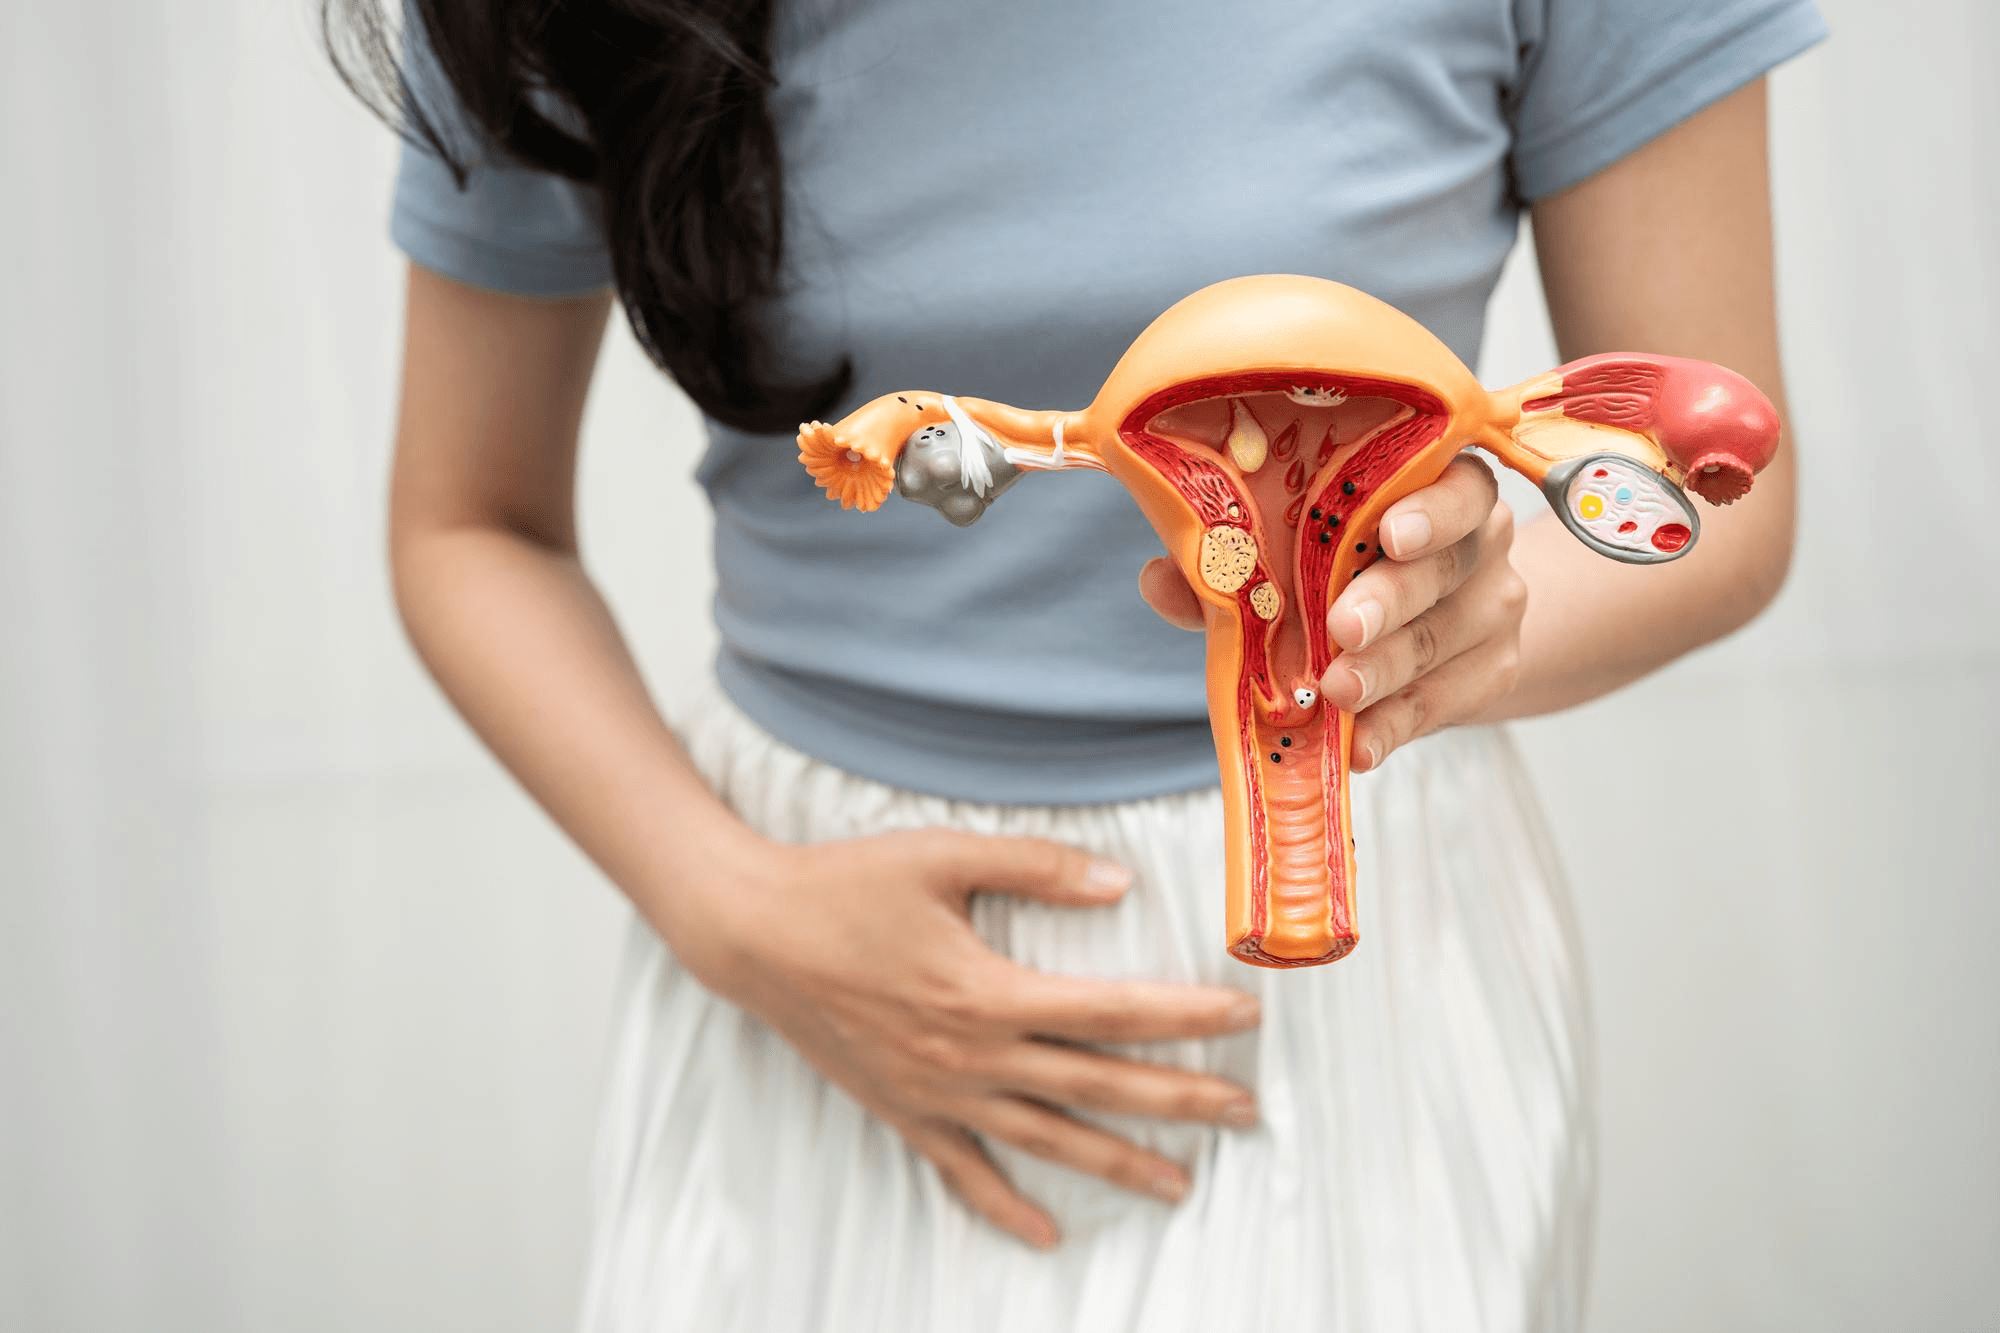
A bicornuate uterus has a dip at the top that gives it a heart-shaped outline.
It often begins with a routine scan. The sonologist pauses, frowns slightly and says, "Your uterus looks heart-shaped. You may have a bicornuate uterus."
Then comes the long wait for an appointment, and a hundred questions. Can I get pregnant? Will I miscarry? Will I need a C-section? Did I do something wrong?
Let me start with reassurance. A bicornuate uterus is a variation you are born with. You did not cause it, and it is not an illness. Most women with this shape conceive and go on to have healthy babies. The condition does raise the chance of a few pregnancy complications, and that is why knowing about it and planning with your doctor makes a real difference.
This guide explains what a bicornuate uterus is, how it differs from other uterine shapes (especially the septate uterus), how it is diagnosed, what it means for fertility, pregnancy and delivery, and when treatment is considered. If you want a personal opinion from a gynaecologist in Noida, you will find details at the end.
What is a bicornuate uterus?
A normal uterus is shaped like an upside-down pear, with a single cavity. A bicornuate uterus has a partial division at the top (fundus), so the uterus looks like it has two "horns" (cornua) that share a single cervix and vagina. The outline of the top of the uterus has a visible indentation, like the dip at the top of a heart.
It is one of the Müllerian anomalies, which come from the way the uterus forms in the early weeks of fetal development. A girl's uterus forms when two tubes (the Müllerian ducts) fuse together in the midline. If the fusion is only partial, you end up with a bicornuate uterus. If the fusion is complete but the wall between them fails to dissolve, you get a septate uterus.
Uterine anomalies of some kind are present in a small percentage of women, commonly quoted at around 3 to 5 in 100 in the general population, and a higher share among women with recurrent miscarriage. The bicornuate type is one of the more common among those with a visible anomaly.
There are two forms:
- Bicornuate unicollis: two horns, one cervix
- Bicornuate bicollis: two horns, two cervical canals (less common)
Bicornuate versus septate uterus: why the difference matters
This is the most common confusion, because the cavity looks similar on a scan, yet the two conditions behave differently and are treated differently.
| Feature | Bicornuate uterus | Septate uterus |
|---|---|---|
| Outer (external) shape of the fundus | Indented, heart-shaped | Normal, smooth, convex |
| Inside | Two cavities with a deep division | A wall (septum) divides the cavity |
| Cause | Incomplete fusion of the ducts | Failure of the wall to dissolve |
| Main risk | Preterm birth, breech position | Miscarriage, especially early |
| Surgery | Rarely needed | Simple hysteroscopic removal often helps |
The key is to look at the outside contour of the uterus. A fundal indentation of more than about 1 cm suggests bicornuate. A flat or only slightly dipping fundus suggests septate. That cannot be seen reliably on a basic scan, which is why the right imaging matters. Mistaking the two can lead to the wrong treatment, for example, surgery on a bicornuate uterus that doesn't need it.
What symptoms does it cause?
Many women have no symptoms at all and learn about it by chance, during a scan for another reason, an IVF work-up, a caesarean or after a miscarriage.
Some women notice:
- Painful or heavy periods
- Pain during intercourse
- Recurrent miscarriages or preterm births
- Difficulty with tampon use if there is also a vaginal septum
- Unexplained pelvic pain
It is also worth knowing that uterine anomalies often go with kidney anomalies, such as a missing kidney or a kidney in the wrong place, because the urinary and genital systems form close together. Your doctor may recommend an ultrasound of your kidneys.
How is it diagnosed?
A diagnosis combines a history, examination and imaging.
- Pelvic ultrasound. A standard 2D ultrasound may raise suspicion.
- 3D ultrasound. This is the most useful and readily available test. It shows the uterus from the front, including both the cavity and the outer contour, and can often distinguish bicornuate from septate.
- MRI of the pelvis. Provides detailed images of the uterine shape and of the cervix, vagina and kidneys. Often used when the 3D scan is unclear or when surgery is being considered.
- Hysterosalpingography (HSG). Shows the cavity but not the outside of the uterus, so on its own it can't separate bicornuate from septate.
- Hysteroscopy and laparoscopy. A combined procedure that lets the doctor look inside the cavity and at the outside of the uterus. Usually reserved for cases where the diagnosis is uncertain or a surgical decision is being made.
Will it affect fertility?
For most women, getting pregnant is not a problem. Women with a bicornuate uterus ovulate normally, and the tubes and ovaries are usually normal. Chances of natural conception are similar to other women. The cause of any delay in conceiving should be looked for in the same way as anyone else: ovulation, tubes, semen quality and other factors.
Some studies suggest slightly lower implantation or pregnancy rates in uterine anomalies, but the effect, if any, is modest in bicornuate uterus compared with some other types. IVF works in the usual way.
Pregnancy risks with a bicornuate uterus
Here the honesty matters. A bicornuate uterus can increase the chance of certain complications compared with a normal uterus, but the risks apply to a minority, and many of them can be managed.
Miscarriage. The risk of first-trimester miscarriage is somewhat higher than normal, though lower than in a septate uterus. The risk of second-trimester loss is higher than in the general population, mainly through cervical weakness or reduced space.
Preterm birth. This is the main concern. The uterus has a smaller cavity and may contract earlier, so delivery before 37 weeks is more common than average. Studies show the rate of preterm birth is significantly raised, though many women still deliver at term.
Malpresentation. The baby is more likely to lie in a breech or transverse position because the shape of the cavity does not guide the head down. This is a common reason for a caesarean in these pregnancies.
Fetal growth restriction. Reduced room or blood supply can slow growth in some cases.
Cervical insufficiency. A weak cervix that opens early can occur and may need a stitch (cerclage).
Placental problems. Slightly higher rates of abruption and retained placenta are reported.
Caesarean delivery. Higher than average, mostly because of baby position, preterm labour or fetal distress.
None of this means you will experience any of these. It means your pregnancy deserves attentive follow-up.
How pregnancy is managed
A well-planned antenatal programme makes a large difference. Depending on your history, I may recommend:
- An early scan to confirm the position of the pregnancy in the uterus
- Cervical length measurements by transvaginal scan from around 16 to 24 weeks, to catch a short cervix early
- Cerclage or progesterone if your cervix is short or you have had earlier second-trimester losses or preterm birth. This is decided individually
- Regular growth scans from the third trimester, since growth may be affected
- Position checks near term to plan delivery
- Attention to warning signs such as regular tightening, backache, leaking fluid or bleeding
You will also be advised to be aware of preterm labour signs, avoid heavy work and keep regular check-ups. Bed rest has not been shown to prevent preterm birth, so it is not routinely recommended.
Delivery: can I have a normal delivery?
Yes, many women with a bicornuate uterus have a normal vaginal delivery, particularly when the baby is head-down and labour starts spontaneously at term. The decision depends on:
- The baby's position
- Whether there was previous uterine surgery
- Fetal growth and wellbeing
- How labour progresses
A caesarean section is often needed if the baby is breech or transverse, or if labour does not progress. Delivery should take place in a hospital with facilities for emergency care and neonatal support. A planned conversation in the third trimester will help you know what to expect.
When is treatment or surgery needed?
For most women, no treatment is necessary. Surgery for a bicornuate uterus is rare and reserved for specific situations.
Strassman metroplasty is an operation that joins the two cavities into one. It is considered only if a woman has had recurrent pregnancy loss or preterm births clearly attributed to the bicornuate uterus after other causes are excluded, and after careful counselling. The surgery carries risks, including scarring, and needs a caesarean for all future deliveries. So it is not routine.
Surgery is quite different for a septate uterus, where removing the septum through a simple hysteroscopy is common and effective. That is why correct diagnosis matters.
Other problems that may accompany a bicornuate uterus, such as an obstructed horn or a vaginal septum, may need their own treatment.
Living with a bicornuate uterus
Some practical points:
- Tell every doctor who looks after you, including emergency doctors, so it is documented.
- Don't let it scare you. Many women never run into trouble.
- Plan early. If you are trying to conceive, a pre-conception visit lets us review your scans, rule out other causes of difficulty and plan your care.
- Look after the basics. Folic acid, a balanced diet, a healthy weight and avoiding smoking all support a healthy pregnancy.
- Seek support. If you have had pregnancy losses, a gentle, specialist team makes a difference.
Questions women ask me
Is a bicornuate uterus the same as a double uterus? No. A double uterus (uterus didelphys) has two separate uterine cavities and often two cervices. It is a different anomaly.
Can I carry twins in each horn? Twin pregnancies can occur, and they are considered high risk.
Can it be corrected without surgery? There is no non-surgical way to change the shape. Fortunately, most women do not need correction.
Does it run in families? Usually not, though a few families show clusters.
Will it affect my periods? Often not. Some women have heavier or more painful periods.
Can I have a vaginal birth after a caesarean (VBAC)? This depends on the type of previous uterine incision and the reason for the caesarean. It is a case-by-case decision.
Get a clear diagnosis and a plan
If you have been told that you have a "heart-shaped" or abnormal uterus, the first step is an accurate diagnosis, ideally with a 3D scan or MRI. The next is a plan that suits your age, your history and your wishes. I see women from Noida, Greater Noida, Ghaziabad and Delhi NCR at Prakash Hospital, Sector 33. To book a consultation, call +91 97023 46853.
Related reading
- Septate uterus: miscarriage risk and treatment
- Recurrent miscarriage: causes and tests
- Cervical incompetence and cerclage
- Hysteroscopy vs laparoscopy
- High-risk pregnancy care
This article is for general education. It does not replace advice from your own doctor.













