Letrozole for Ovulation Induction: How It Works and How It Differs from Clomid
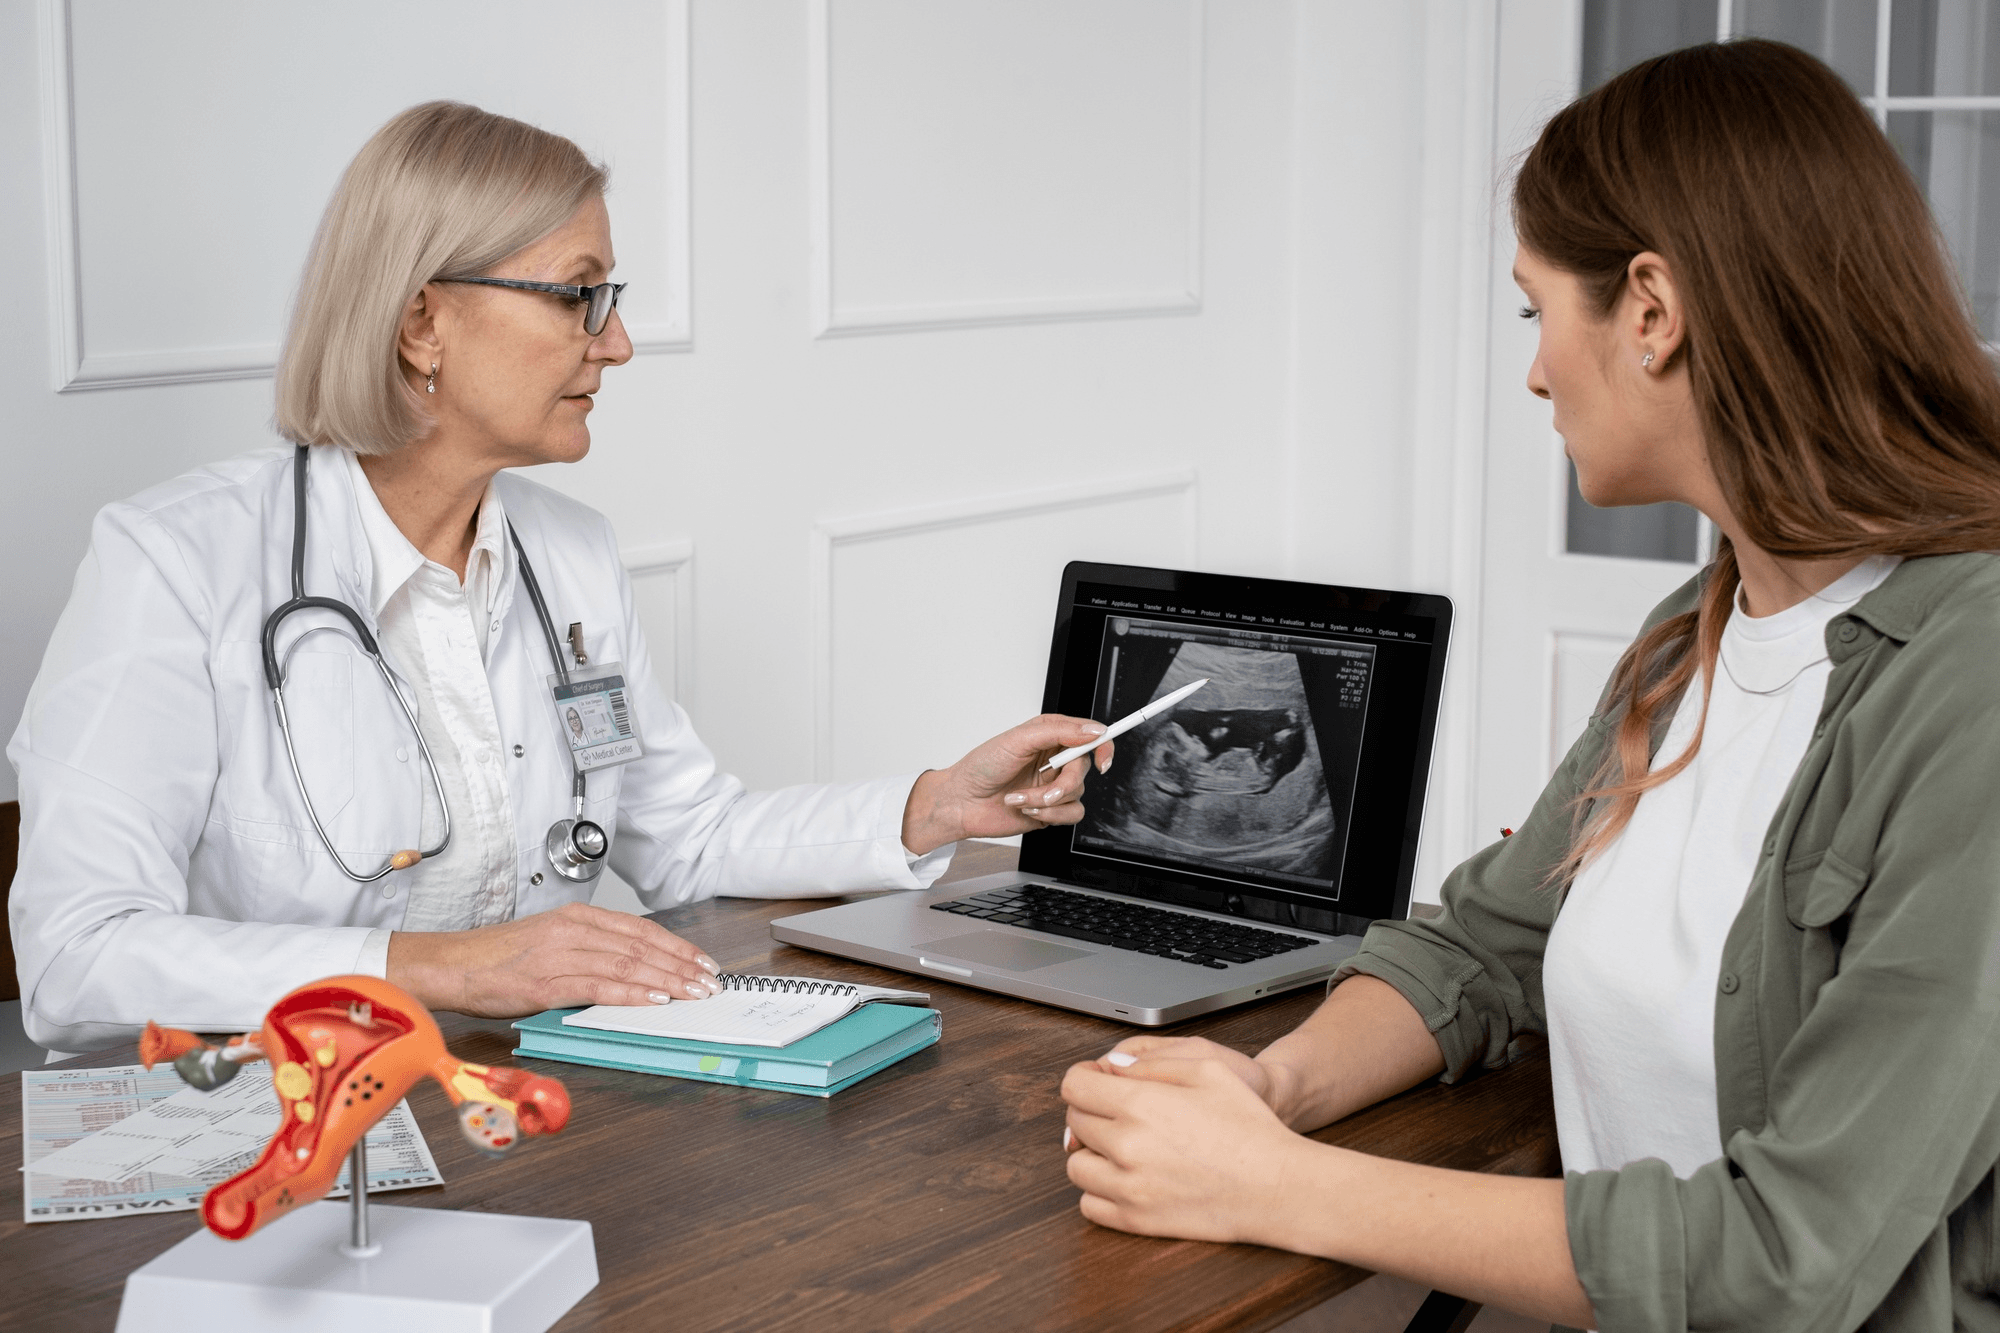
A follicle scan around day 10 to 12 shows whether letrozole has made a follicle grow.
If you have PCOS or irregular ovulation and have been trying to conceive, you may have heard two names from friends, forums and doctors: clomiphene (Clomid) and letrozole. Some people say letrozole is "stronger." Others say it is "just the new fashion." A few have read online that it is only for breast cancer and wonder whether it is even safe.
Let me clear this up. Letrozole is an established, widely used medicine for inducing ovulation, and in women with PCOS, the best available evidence suggests it often works better than clomiphene. It is not a magic tablet, and it still needs a proper diagnosis and monitoring. This guide explains how it works, who benefits, how it compares with clomiphene, side effects and risks, and what a treatment cycle looks like. If you are looking for a gynaecologist in Noida for ovulation induction, details are at the end.
What is letrozole?
Letrozole belongs to a group of medicines called aromatase inhibitors. Aromatase is an enzyme that converts androgens into oestrogen. Letrozole was developed and approved for treating hormone-sensitive breast cancer in postmenopausal women, by lowering oestrogen levels.
Doctors noticed that the same effect could be used in fertility. When oestrogen drops briefly in the early part of the cycle, the brain senses it and increases the release of FSH, the hormone that makes follicles grow. The result is stimulation of the ovaries to develop a mature follicle and ovulate.
Using letrozole for ovulation induction is called off-label, meaning it is not the original licensed use. Off-label does not mean unsafe or experimental. Many standard medicines are used this way, and letrozole has been used for ovulation induction for over two decades, with a large body of research behind it. Your doctor should explain this to you openly.
How is it different from clomiphene?
Both are tablets taken for five days early in the cycle, and both aim to trigger ovulation. They work differently.
| Clomiphene citrate | Letrozole | |
|---|---|---|
| How it works | Blocks oestrogen receptors in the brain, so it "thinks" oestrogen is low | Reduces oestrogen production, which raises FSH |
| Effect on uterine lining | May thin the lining and cervical mucus | Usually does not thin the lining |
| Half-life | Long (days), lingers in the body | Short (about two days), clears quickly |
| Twin risk | Around 5 to 8 percent | Lower in most studies, often 3 to 4 percent or less |
| Best studied in | Many groups | PCOS and unexplained infertility |
| Typical side effects | Hot flushes, mood swings, visual symptoms | Fatigue, dizziness, headache, hot flushes |
The practical advantages of letrozole are that it tends to produce one or two mature follicles, rarely causes the antioestrogen effect on the lining and mucus and often works in women who did not respond to clomiphene.
What does the research show?
The best-known study is a large American trial of women with PCOS (published in 2014 in the New England Journal of Medicine). It compared letrozole with clomiphene for up to five cycles. Live birth rates were higher with letrozole (around 27 percent against about 19 percent for clomiphene over the treatment period). Ovulation rates were also higher. Other studies and reviews have reached similar conclusions, and many international guidelines now recommend letrozole as a first-line treatment for ovulation induction in PCOS.
For women with unexplained infertility, the evidence is more mixed. Letrozole is still used, often with IUI. For women who do not have an ovulation problem, treatment is less clearly beneficial.
These are group results. Individual response varies a lot, and your age, weight, other fertility factors and your partner's sperm also matter.
Who might benefit?
- Women with PCOS and irregular or absent ovulation. This is the main group.
- Women who did not ovulate or did not conceive on clomiphene, or in whom clomiphene thinned the lining or caused unpleasant side effects.
- Women with unexplained infertility, sometimes combined with IUI.
- Women with a thin endometrium on clomiphene.
- Cycles preparing for frozen embryo transfer, where letrozole is sometimes used to stimulate a natural-type cycle.
- Women with endometriosis or fibroids under hormone-sensitive management, in selected cases (this is a specialist decision).
Who may not benefit?
- Women with blocked fallopian tubes, since ovulating does not help if the egg cannot meet the sperm
- Couples where a severe male factor is the main problem
- Women with very low ovarian reserve or premature ovarian insufficiency, who might not respond
- Women who are pregnant or may be pregnant. Letrozole must not be taken in pregnancy, so a pregnancy test is checked before starting
- Women who are breastfeeding
- Anyone with an allergy to the drug
That's why a basic fertility evaluation should come first: ovulation tracking, hormone tests, a pelvic ultrasound, a tubal assessment where appropriate and a semen analysis for your partner.
What does a letrozole cycle look like?
Your doctor decides the dose and schedule, so I will describe the general pattern, not give exact numbers.
- Baseline check. A pregnancy test and sometimes a scan on day 2 or 3 of your period to make sure there is no cyst or other problem.
- Tablets for five days. Usually taken from about day 2 or 3 until day 6 or 7 of the cycle, once a day, at a dose your doctor selects. If you do not respond, the dose may be increased in the next cycle.
- Follicular monitoring. A transvaginal ultrasound around day 10 to 12, sometimes repeated, shows how many follicles are growing, their size and the thickness of the lining. This is what tells us whether the treatment is working.
- Trigger and timing. When a follicle reaches about 18 to 20 mm, a trigger injection (hCG) may be given to time ovulation, and intercourse or an IUI is planned about 24 to 36 hours later. Some couples simply have timed intercourse without a trigger.
- Luteal support. Progesterone may be given after ovulation in some women.
- Pregnancy test about two weeks after ovulation or when your period is due.
If you do not ovulate at one dose, your doctor may step up the dose in the following cycle. Most guidelines suggest up to about six ovulatory cycles before reassessing and considering other options such as injections, IUI or IVF.
Side effects
Letrozole is generally well tolerated. Possible effects include:
- Tiredness or fatigue
- Dizziness or light-headedness
- Headache
- Hot flushes
- Nausea
- Mild bloating or breast tenderness
- Joint or muscle aches
- Mood changes
These are usually mild and settle after the five days. Tell your doctor if any are severe.
Risks and common worries
Is it safe for the baby? In 2005, a small conference abstract suggested a higher rate of birth defects with letrozole, which created lasting fear. Later and larger studies, including the major PCOS trial, did not confirm that. Most current evidence shows no increase in major malformations compared with clomiphene or with natural conception in babies of women with infertility. Letrozole has a short half-life and clears from the body within a few days, well before an embryo implants. Still, it must not be taken once pregnant.
Multiple pregnancy. The chance of twins is lower than with clomiphene, though not zero. Monitoring by ultrasound reduces the chance of unexpected multiples.
Ovarian hyperstimulation syndrome (OHSS). Rare with oral letrozole alone.
Miscarriage and ectopic pregnancy. The rates are similar to other fertility treatments and to the background risk in women with infertility.
Long-term cancer risk. There is no evidence that short courses of letrozole for ovulation induction increase cancer risk. Its use in breast cancer relates to a different purpose and duration.
Letrozole and PCOS: what else helps?
Medicine works best alongside general measures.
- Weight management. Even a modest 5 to 10 percent weight loss can restore ovulation in overweight women with PCOS and improve response to treatment.
- Exercise and diet to improve insulin resistance.
- Metformin, in selected women with insulin resistance, sometimes alongside ovulation induction.
- Treat other factors like thyroid disease, high prolactin and male-factor issues.
- Folic acid before conception.
Why not just buy it from a chemist?
Tablets are easily available, and some women self-prescribe after reading a forum. I advise against this. Without a scan, you do not know whether you have ovulated, whether more than one follicle has grown or whether you were right to take it at all. Time is also precious. I have seen women take tablets for many months before discovering blocked tubes or a partner's low sperm count. The medicine is only part of care.
When to stop and move on
Reassess your plan if:
- You haven't ovulated despite adjusting the dose
- You have ovulated for 3 to 6 cycles without pregnancy
- You are older, where time matters more
- Another problem shows up on investigation
Next steps can include adding IUI, gonadotropin injections, laparoscopic or hysteroscopic correction of a problem, or IVF. Our articles on IUI and IVF explain these.
Common questions
Can I take letrozole and clomiphene together? Sometimes used in sequence or combination in selected cases under close supervision, but not routinely.
Does letrozole make periods heavier? It may cause a withdrawal bleed or a normal period afterwards.
Will I get pregnant on the first cycle? Some do. Many need several cycles. The chance per cycle is moderate, not certain.
Can it be used for men? Occasionally in specific hormonal patterns under specialist care.
Does it work for women over 40? Success depends largely on egg quality and number, which declines with age. Time matters.
Do I need an injection too? Not always. The trigger is chosen case by case.
Make a plan based on your tests
Choosing between clomiphene and letrozole is a medical decision that depends on your diagnosis, history and response. I see couples from Noida, Greater Noida, Ghaziabad and Delhi NCR for ovulation induction and fertility counselling at Prakash Hospital, Sector 33. To book a consultation, call +91 97023 46853.
Related reading
- Clomiphene citrate: how it works and side effects
- Ovulation induction: what to expect
- PCOS and infertility
- IUI vs IVF
- How to get pregnant fast
This article is for general education. Please do not start or stop medicines without your doctor's advice.