Failed IVF Cycle: Why It Happens and What to Do Next

Most clinics advise waiting one or two menstrual cycles after a failed cycle before trying again.
The call or the blood test result comes, and it is negative. After weeks of injections, scans, waiting rooms and hope, all the effort seems to have ended in a single line on a report. For many couples, a failed IVF cycle feels like grief. It can bring anger, guilt, numbness, exhaustion and a heavy question: what did we do wrong?
Let me say first, as plainly as I can: it is almost never anything you did. You did not fail because you walked too much, ate the wrong food, felt stressed or didn't rest enough. IVF is a good treatment, but it is not a guaranteed one, and even with perfect embryos and a perfect lab, a single transfer succeeds less than half the time for many couples.
This guide explains why IVF cycles fail, how doctors review a failed cycle, what tests and changes might help, what your realistic chances look like and how to look after yourselves. If you are looking for a fertility specialist in Noida for a second opinion or next steps, details are at the end.
First, give yourselves time
Before any analysis, acknowledge what has happened. A failed cycle is a loss: of hope, of the embryo you imagined and of the plan you had. Allow time to grieve. There's no rule about how long, but most clinics advise waiting for one or two menstrual cycles before the next attempt, partly to let your body recover and partly to allow a proper review. If you need longer, that is fine.
Talk to your partner. Men often feel left out or want to stay strong, and may not show how hurt they are. Seek support from a counsellor, a support group or a trusted friend. Many clinics offer counselling.
How common is IVF failure?
Success depends heavily on age and diagnosis, and no number applies to everyone. In general:
- For women under 35, the chance of a live birth per fresh or frozen transfer is roughly 40 to 50 percent in good programmes, per transfer of a good-quality embryo
- It declines gradually with age, and is much lower after 40 because of reduced egg quality
- Cumulative success across several transfers from one egg collection is higher than the success of a single transfer
So even in the best circumstances, many cycles do not end in pregnancy. Failure at the first attempt is common, not an exception.
What does "failed IVF" mean?
The phrase covers several different situations.
- Poor response to stimulation. Few follicles or eggs develop, or the cycle is cancelled.
- No fertilisation. Eggs and sperm combined, but none fertilise.
- Poor embryo development. Embryos stop growing before they can be transferred.
- Implantation failure. Embryos are transferred, but no pregnancy occurs (negative test).
- Biochemical pregnancy. A positive blood test, followed by a falling hCG and a period. This is an early pregnancy loss.
- Early miscarriage. A pregnancy that is seen on scan but not continuing.
Each has different causes and different next steps, so being clear on which one you had matters.
Why do IVF cycles fail?
Often, there is no single explanation. The most common reasons are the following.
1. Embryo chromosome abnormalities
This is the commonest reason for failed implantation and early miscarriage. Many embryos, even those that look good under the microscope, carry the wrong number of chromosomes (aneuploidy). The rate rises sharply with the woman's age: a majority of embryos from women in their late thirties and forties are chromosomally abnormal. Nothing you did caused this. It is a natural feature of egg biology.
2. Egg quality and ovarian reserve
Fewer eggs, and eggs of lower quality, reduce the number of good embryos available. This is age-related but can also occur in younger women with low ovarian reserve.
3. Sperm factors
Poor sperm quality, high DNA fragmentation or unrecognised problems can impair fertilisation and embryo development.
4. Uterine factors
- Polyps, fibroids that distort the cavity
- Intrauterine adhesions (Asherman's syndrome)
- A septate uterus or other congenital anomalies
- Thin endometrium
- Adenomyosis
- Chronic endometritis, a low-grade inflammation
- Fluid in the cavity
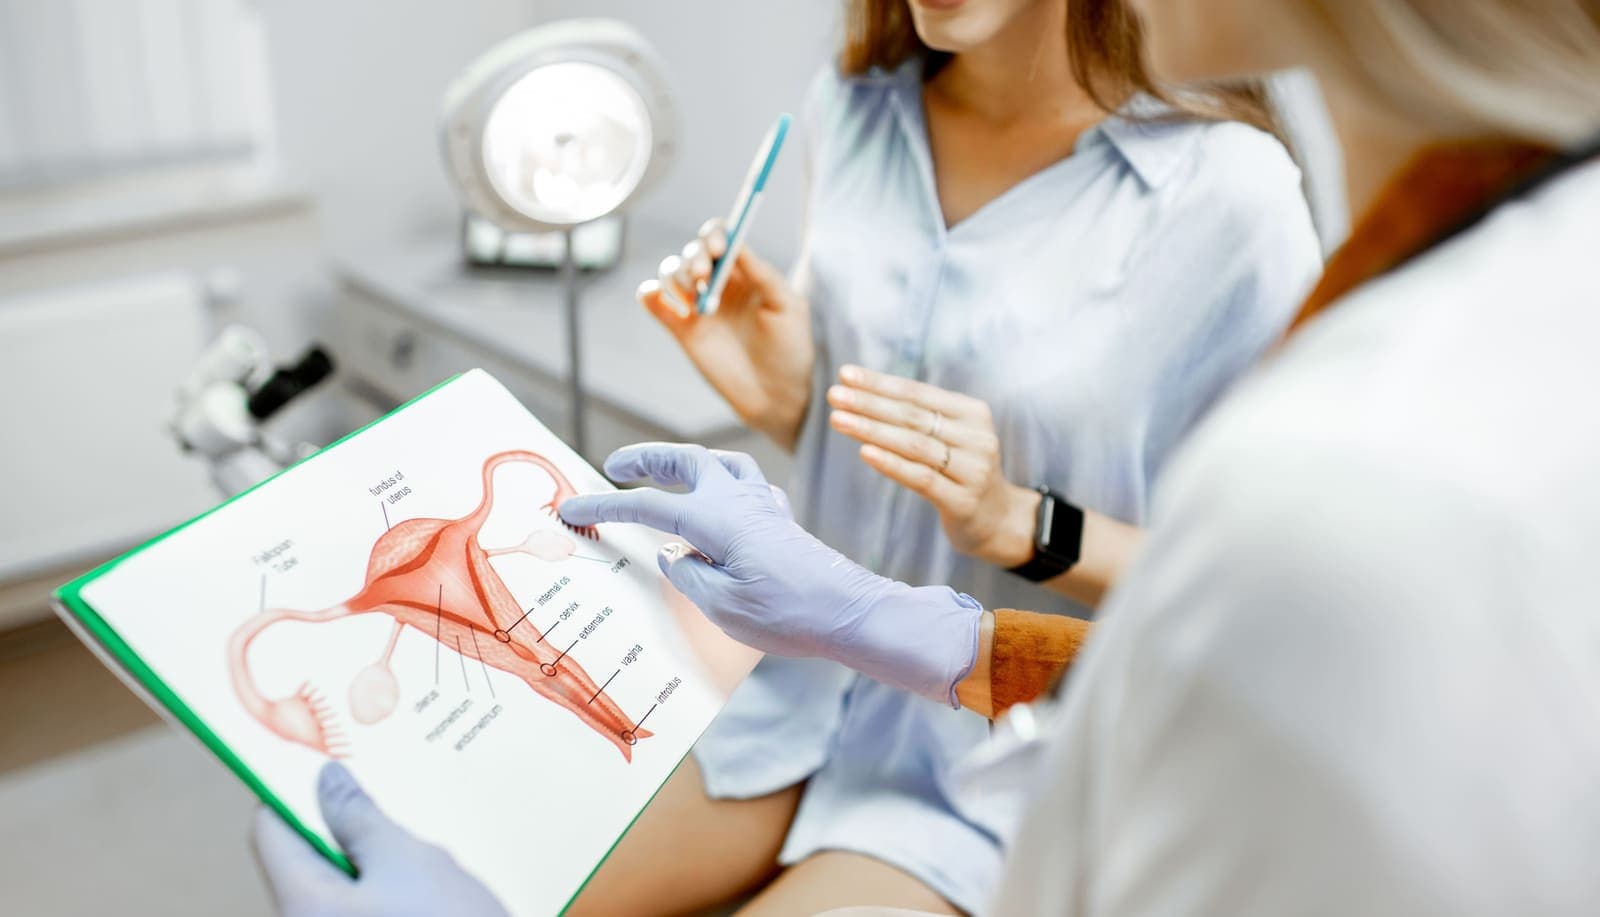
5. Tubal factors
A hydrosalpinx (a blocked, fluid-filled tube) can leak toxic fluid into the uterus and lower implantation rates. Surgery to remove or block the tube before IVF improves success.
6. Receptivity of the endometrium
The lining has a "window of implantation," a limited time when it's ready to accept the embryo. In some women the window may be shifted. Tests exist to look for this, though their value is debated.
7. Hormonal and metabolic factors
Uncontrolled thyroid disease, diabetes, high prolactin or low progesterone support can all reduce the chance of success. Obesity, smoking and heavy alcohol use reduce IVF outcomes.
8. Immunological and clotting factors
The role of immune abnormalities and inherited clotting disorders (thrombophilias) in repeated IVF failure is controversial. Antiphospholipid syndrome is a recognised cause of pregnancy loss and is treatable, but many other proposed immune tests and treatments lack strong evidence.
9. Laboratory and technical factors
The skill of the embryologist, culture conditions and the transfer technique all matter. A difficult transfer, such as a very curved cervix or bleeding, can affect implantation.
10. Pure chance
Sometimes everything is fine, the embryo is good, the uterus is receptive and implantation just does not occur on that attempt.
What should happen after a failed cycle? The review
A good clinic will offer a follow-up consultation to go through the cycle in detail. Expect to discuss:
- Response to stimulation: number of follicles, eggs collected, mature eggs
- Fertilisation rate: how many eggs fertilised, and by what method (IVF or ICSI)
- Embryo development: how many reached the blastocyst stage, and their quality grade
- Transfer details: how many embryos, which day, ease of transfer, lining thickness
- Hormone support and timing
- Your history, and anything that was missed or changed
The aim is to see whether the problem looks like eggs, sperm, embryos, uterus or an unexplained failure, and then to decide on changes.
Tests worth considering
Not every test is needed for every couple. Reasonable options after one or two failures include:
- Hysteroscopy, to look directly at the uterine cavity and treat polyps, adhesions or a septum
- 3D ultrasound or saline sonography for uterine shape
- Assessment of the tubes for hydrosalpinx
- Semen re-analysis and sperm DNA fragmentation testing in selected cases
- Ovarian reserve review (AMH, antral follicle count)
- Thyroid, prolactin and blood sugar checks
- Karyotype of both partners (chromosome testing), particularly with a history of miscarriage or poor embryo development
- Endometrial biopsy for chronic endometritis, and treatment with antibiotics when present
- Thrombophilia and antiphospholipid antibody testing if there's a relevant history
- Preimplantation genetic testing for aneuploidy (PGT-A) in some cases, to select chromosomally normal embryos
- Endometrial receptivity testing (ERA). Its benefit remains uncertain, so discuss the evidence carefully
Beware of long lists of add-on tests and treatments offered without a clear rationale. Good doctors explain the evidence honestly, including when it is weak.
Changes that might improve the next cycle
Depending on the findings, your doctor may suggest:
- Adjusting the stimulation protocol to improve egg number or quality
- Switching to ICSI if fertilisation was poor
- A freeze-all strategy with a frozen embryo transfer in a later, prepared cycle
- Extended culture to the blastocyst stage to select better embryos
- Treating a uterine or tubal problem found on investigation
- Preimplantation genetic testing in selected couples, understanding its limits
- Optimising lifestyle: weight, smoking, alcohol, sleep and stress
- Treating male factors (varicocele, lifestyle, medicine) and considering sperm selection methods
- Using donor eggs, donor sperm or donor embryos where the underlying cause is severe egg or sperm limitation
- Considering a gestational carrier in cases of absent or severely abnormal uterus (regulated by law in India, with strict legal requirements)
- Adoption or living child-free as valid choices for some couples
Ineffective or unproven add-ons, such as endometrial scratching routinely, immune therapies such as intralipid or steroids without clear indication, or extra supplements, may be offered by some clinics. Ask for the evidence.
How many cycles should you try?
There is no universal answer, but the data are encouraging for many. In good-prognosis couples, cumulative live birth rates increase with each additional transfer, with many pregnancies occurring in the second or third attempts. For women over 40, or with very low ovarian reserve, the chance per cycle is lower, so it may be more useful to look at alternatives such as donor eggs earlier. The decision depends on your age, your embryo results, your emotional and financial resources and your own values. A frank conversation about "how many tries and when do we reassess" is helpful.
Taking care of yourselves
- Allow time to grieve. Cry if you need to.
- Avoid self-blame. Replaying what you did in the two-week wait is natural, and it is not the cause.
- Rest your body. Gentle exercise, good sleep and nutritious food help.
- Reconnect as a couple. Fertility treatment can strain intimacy and communication. Plan activities not related to treatment.
- Limit comparisons and unwanted advice. Well-meaning relatives can say hurtful things. It is fine to set boundaries.
- Consider counselling with someone who understands infertility.
- Take a break if needed. Pausing treatment for a few months to recover emotionally is acceptable.
- Watch for signs of depression or anxiety, such as persistent low mood, loss of interest, hopelessness or trouble sleeping. Seek help.
Common questions
Did I fail because I was stressed? No. Stress hasn't been shown to determine IVF success.
Did I rest too little? No. Bed rest doesn't improve outcomes.
Will the next cycle work? No one can promise, but many couples succeed in later attempts, especially when a specific cause is found and corrected.
Should we change clinics? If you lack confidence in your team, if communication is poor or if no review was offered, a second opinion is reasonable. Bring all your reports.
How soon can we try again? Often after one or two cycles, depending on your recovery and the review.
Is a biochemical pregnancy a failure? It is a very early loss. It shows that implantation can occur, which many doctors consider encouraging, though it is painful.
You do not have to figure this out alone
A failed IVF cycle is hard, but it also gives information. With a careful review, many couples find a clearer path. I see couples from Noida, Greater Noida, Ghaziabad and Delhi NCR for second opinions and fertility counselling at Prakash Hospital, Sector 33. To book a consultation, call +91 97023 46853.
Related reading
- Questions to ask before IVF
- Frozen embryo transfer: process and success
- Embryo transfer and the two-week wait
- Thin endometrium: causes and treatment
- Unexplained infertility
This article is for general education. Decisions about further treatment should be taken with your fertility specialist.