Fetal Growth Restriction: What It Means When Your Baby Is Measuring Small

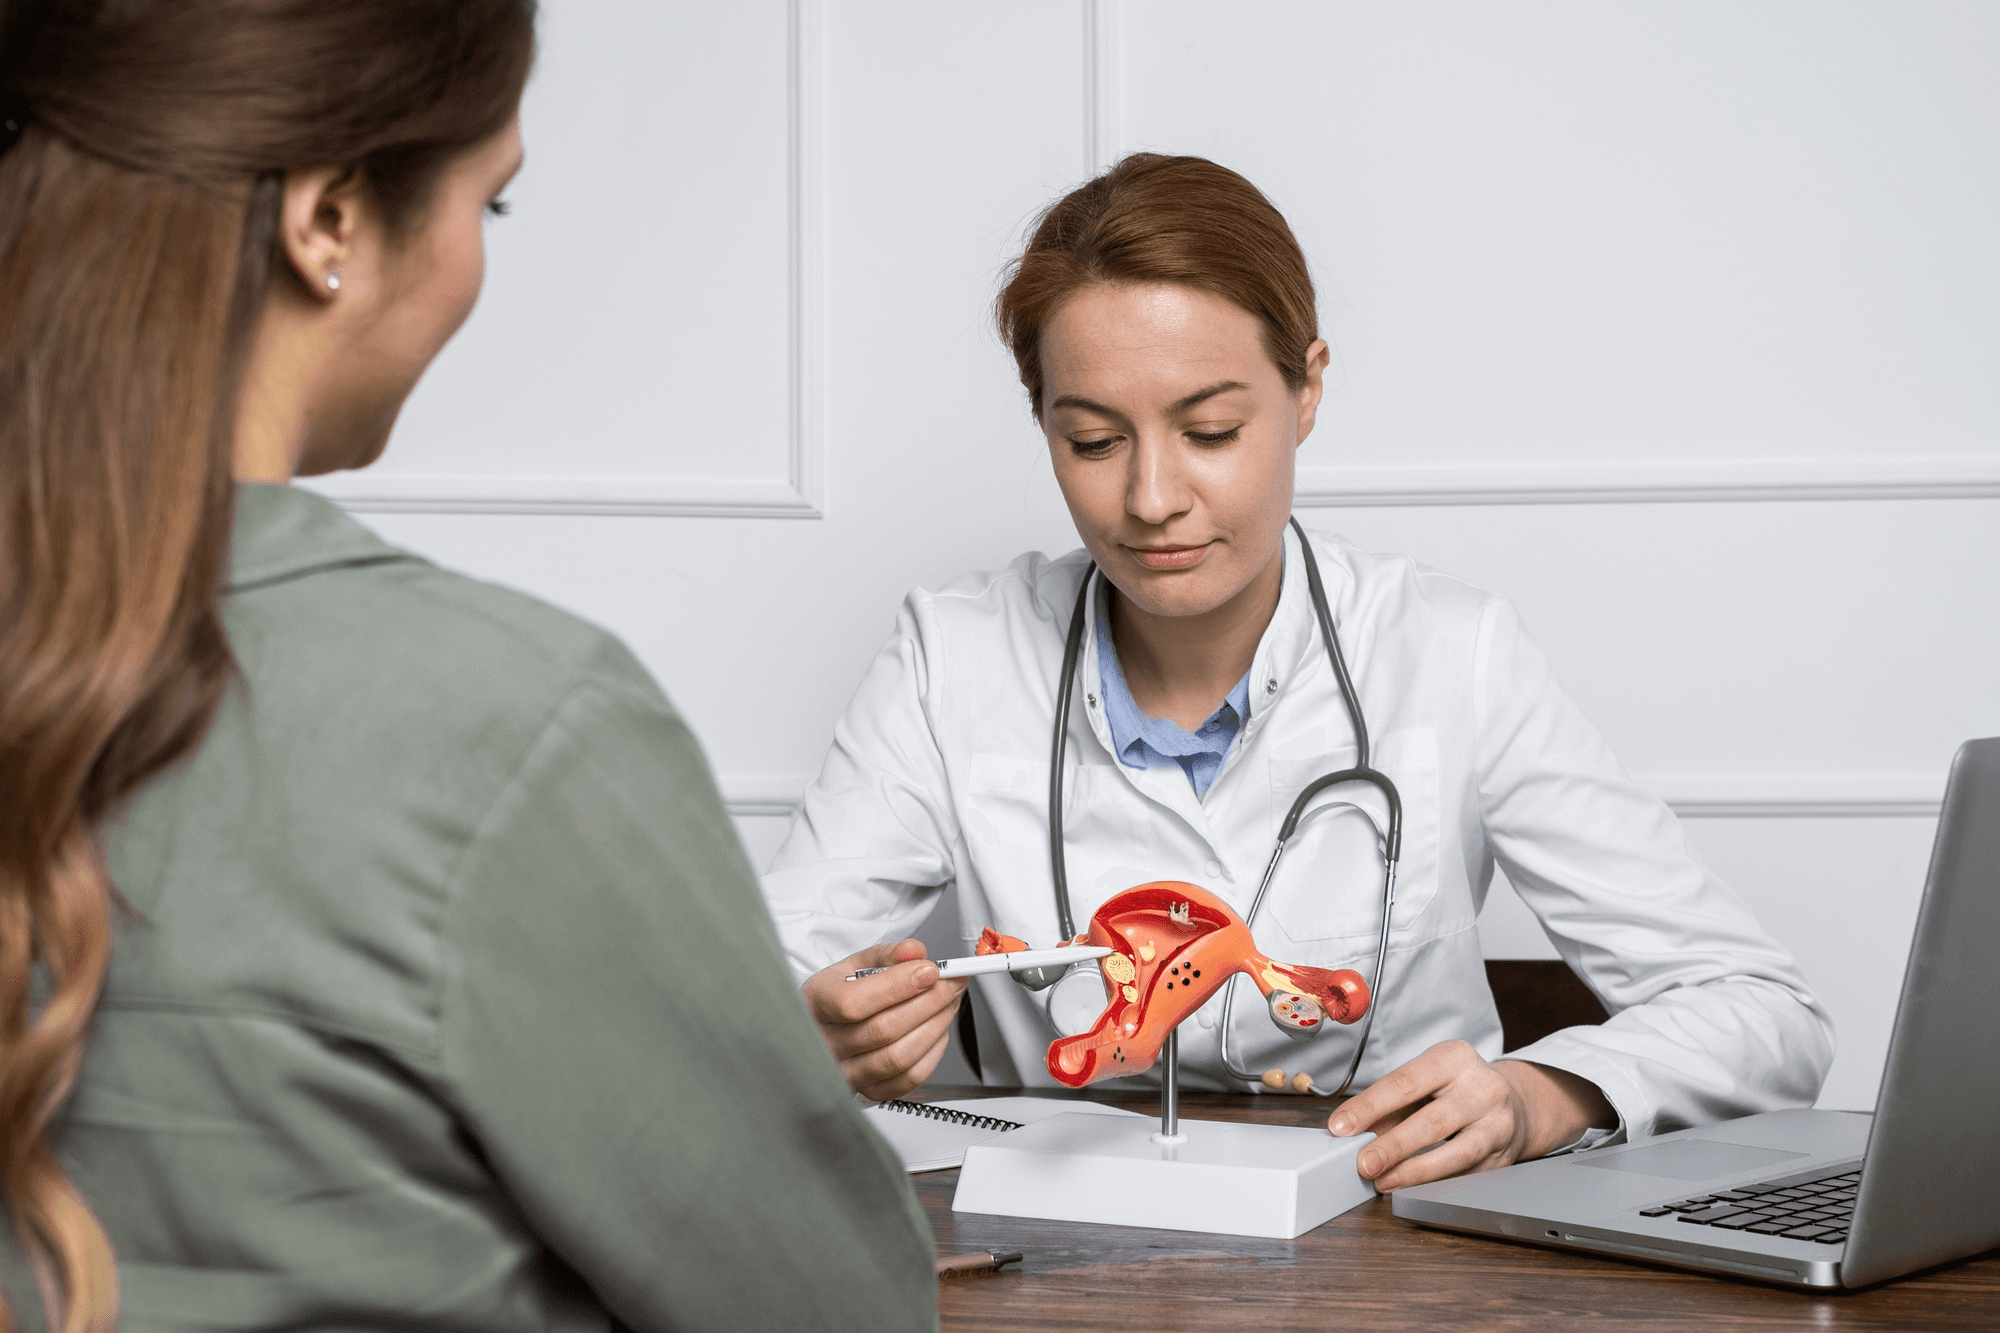
Gynecologist conducting routine prenatal checkup with pregnant woman, ensuring fetal growth, maternal health, and safe pregnancy monitoring.
Being told at a growth scan that your baby is measuring below the expected size for gestational age is understandably alarming. The first thing to understand: small does not automatically mean there is a problem. Some babies are constitutionally small — healthy, growing appropriately for their genetic potential, just at the lower end of the normal range. But some small babies are growth-restricted — failing to reach their growth potential because of placental insufficiency, maternal factors, or fetal problems. Distinguishing between the two is the entire clinical challenge.
Dr. Shachi Singh, consultant obstetrician at Prakash Hospital, Sector 33, Noida, explains.
What Fetal Growth Restriction Is
Fetal growth restriction (FGR) — previously called intrauterine growth restriction (IUGR) — is defined as a fetus that fails to reach its biologically determined growth potential. It is typically defined on ultrasound as an estimated fetal weight or abdominal circumference below the 10th centile for gestational age. Below the 3rd centile defines severe FGR.
But centile alone does not diagnose FGR — a fetus can be below the 10th centile and growing well (constitutionally small), or above the 10th centile and growth-restricted (if the baby was tracking at the 60th centile and has dropped to the 15th). The trajectory — the change in centile over time — and the Doppler blood flow findings are what distinguish pathological restriction from small-normal.
What Causes FGR
Placental causes (most common — approximately 70 to 80% of FGR):
Placental insufficiency — the placenta fails to deliver adequate oxygen and nutrients to the fetus. The placenta grows inadequately, or its vascular resistance is high, reducing effective blood flow. This is the mechanism underlying preeclampsia-associated FGR (preeclampsia and FGR often coexist because they share a common pathology — abnormal placentation from early pregnancy).
Maternal causes:
- Hypertension (chronic and pregnancy-induced)
- Preeclampsia
- Diabetes (particularly with vascular complications)
- Autoimmune conditions — antiphospholipid syndrome, SLE
- Severe anaemia
- Smoking (carbon monoxide reduces fetal oxygen delivery)
- Malnutrition
- Thrombophilias
Fetal causes:
- Chromosomal abnormalities (trisomy 18, 21, 13) — often associated with FGR, particularly early-onset
- Congenital infections: cytomegalovirus (CMV), toxoplasmosis, rubella, syphilis — all can cause placental inflammation and FGR
- Structural fetal abnormalities
- Twin-twin transfusion syndrome in monochorionic twins
Idiopathic: No identifiable cause despite thorough investigation — the largest single group.
How FGR Is Monitored
Ultrasound Growth Scans
Serial growth scans every 2 to 4 weeks, measuring:
- Head circumference (HC)
- Abdominal circumference (AC) — the most sensitive single measurement for FGR (the liver is one of the first organs to sacrifice growth when placental supply is limited)
- Femur length (FL)
- Estimated fetal weight (EFW) — plotted on a centile chart
The AC centile and its trajectory over time are more informative than a single measurement.
Doppler Ultrasound — The Critical Investigation
Doppler ultrasound measures blood flow velocity in specific fetal vessels — reflecting the vascular resistance in the placenta and fetal circulation. This is the most important tool for distinguishing constitutionally small from placentally compromised babies.
Uterine artery Doppler (from 20 to 24 weeks): Elevated resistance (notching) in the uterine arteries indicates poor trophoblast invasion and identifies women at risk of placental insufficiency and preeclampsia before FGR becomes evident.
Umbilical artery (UA) Doppler: Reflects placental vascular resistance. As the placenta deteriorates, resistance rises, eventually causing:
- Elevated PI/RI (pulsatility/resistance index) — early compromise
- Absent end-diastolic flow (AEDF) — significant compromise, typically accelerates monitoring to every 48 to 72 hours
- Reversed end-diastolic flow (REDF) — severe compromise, typically prompts delivery planning urgently
Middle cerebral artery (MCA) Doppler: The fetal brain "steals" blood flow when placental supply is compromised — MCA PI falls (brain-sparing). A low MCA PI in the context of high UA PI is a sign of significant fetal compromise.
Cerebro-placental ratio (CPR): MCA PI divided by UA PI — a sensitive indicator of fetal redistribution, often abnormal before individual Doppler values are clearly abnormal.
Ductus venosus (DV) Doppler: Late marker — absent or reversed DV a-wave indicates imminent fetal decompensation, typically near the threshold for delivery.
CTG (Cardiotocography)
Fetal heart rate monitoring — used increasingly as FGR worsens. Late decelerations and reduced variability are signs of fetal hypoxaemia. CTG is reassuring but not a sensitive early marker of FGR — Doppler is more useful for surveillance.
When to Deliver
Delivery timing in FGR involves balancing the risks of continuing a compromised pregnancy against the risks of prematurity. The decision is based on:
- Gestational age
- Severity of Doppler changes (UA, MCA, DV)
- CTG findings
- Growth trajectory
- Presence of preeclampsia or other complications
- Biophysical profile score
General principles:
- Term FGR with stable Doppler: delivery at 37 to 38 weeks
- Absent UA end-diastolic flow from 34 weeks: delivery at 34 to 37 weeks depending on full clinical picture
- Reversed UA flow: delivery at 32 to 34 weeks
- Abnormal DV: delivery irrespective of gestational age if after 30 weeks
All decisions are highly individualised and require specialist obstetric input.
Obstetric Care in Noida and Greater Noida
Dr. Shachi Singh at Prakash Hospital, Sector 33, Noida, monitors fetal growth with serial scans and Doppler assessment, and manages fetal growth restriction for women across Noida and Greater Noida.
To book a consultation, call: +91 97023 46853
Clinic Hours: Monday to Saturday, 9 AM – 6 PM | Sunday, 10 AM – 2 PM
Address: D-12A, 12B, Sector-33, G.B. Nagar, Noida, UP 201301
This blog is for educational purposes only. FGR management requires individualised obstetric specialist input.